
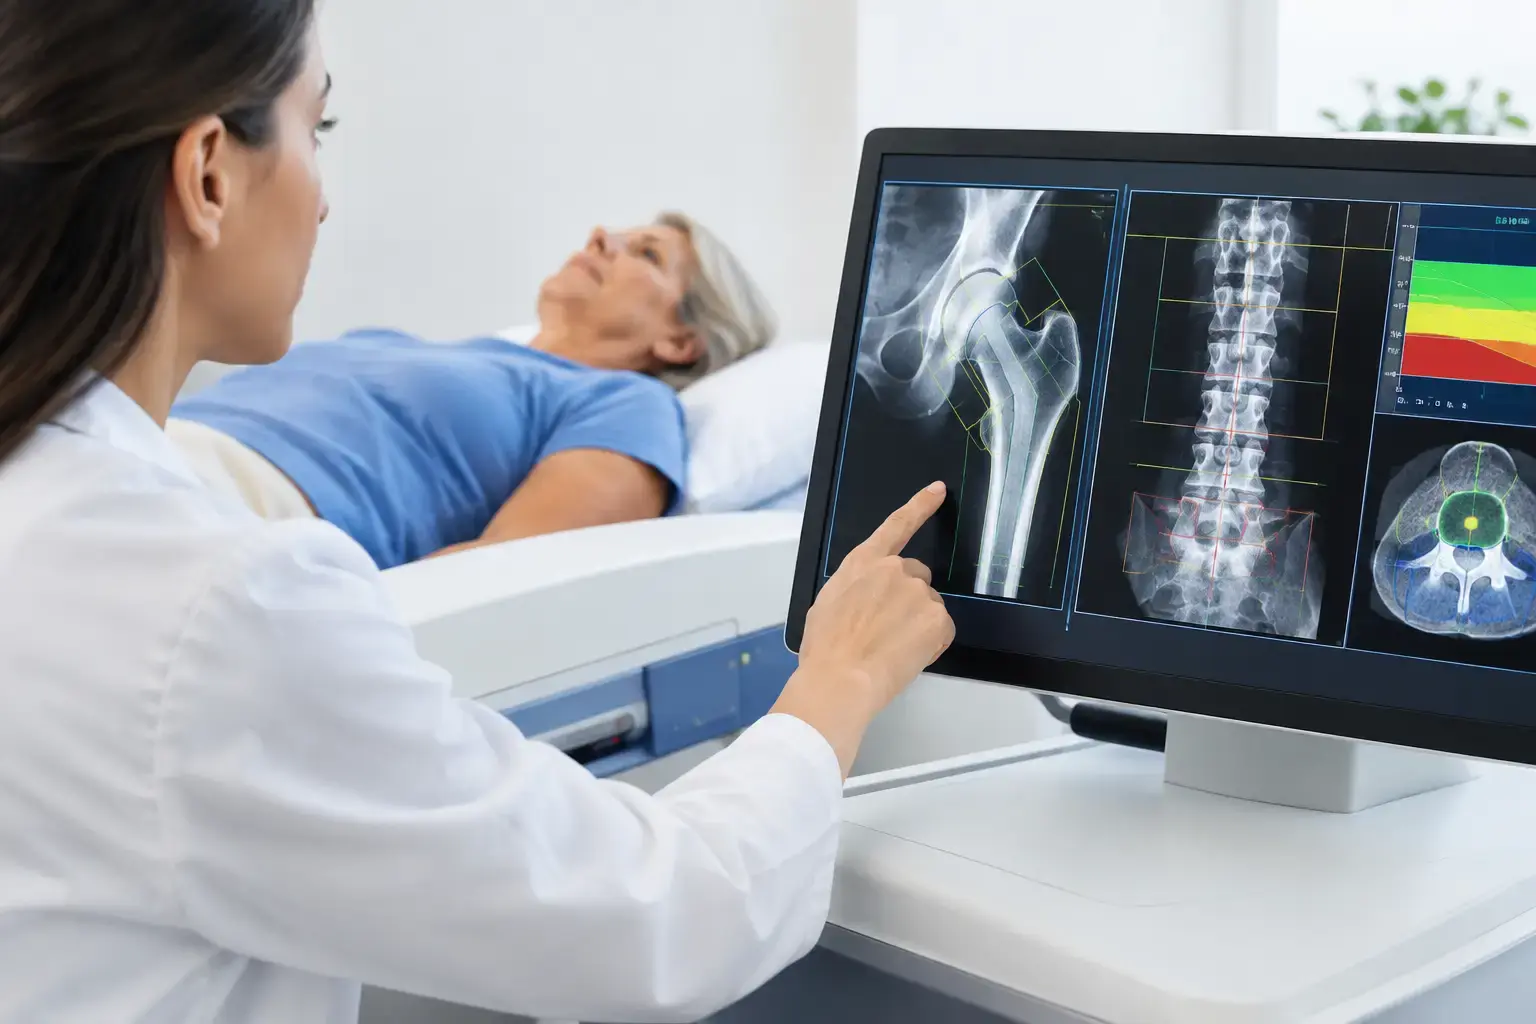
A steroid prescription can solve an urgent problem while quietly changing another part of your health. If you take systemic glucocorticoids such as prednisone for months, steroid bone monitoring gives you a way to see skeletal change before a fracture makes it impossible to ignore.
That matters because glucocorticoid-related bone loss can begin early, often without pain or any outward sign. A density test remains central to the picture. But density alone does not fully explain why two people with a similar result can have different levels of fragility or different fracture risk.
Why steroids affect bone so quickly
Glucocorticoids are powerful anti-inflammatory medicines used for conditions ranging from autoimmune disease and asthma flares to inflammatory bowel disease and cancer-related care. Their benefits can be substantial. The bone effects are real, too, particularly with oral or injected systemic steroids used repeatedly or over longer periods.
Bone is living tissue, continually being renewed. Cells called osteoblasts build bone, while osteoclasts resorb older bone as part of normal remodeling. Glucocorticoids can disrupt that balance by reducing bone formation and, especially early in treatment, increasing bone resorption. They can also affect calcium handling, muscle function, and sex-hormone signaling, all of which matter to skeletal strength and falls.
The result is not merely a lower number on a future scan. It is a change in the biology of bone. Vertebrae in the spine can be particularly vulnerable because they contain more trabecular, or spongy, bone, which remodels faster than the dense outer shell of bone.
Risk is shaped by more than whether steroids appear on your medication list. Dose, duration, repeated courses, the underlying inflammatory condition, age, menopause status, prior fractures, body weight, smoking, alcohol use, and other medications can all change the picture. Inhaled, topical, and short-term steroid use do not carry the same risk profile as sustained systemic exposure, although the details depend on the medication and the person.
What steroid bone monitoring is actually looking for
Monitoring is not one test at one moment. It is a way of establishing a baseline, understanding risk in context, and comparing meaningful measurements over time.
Clinical guidelines for glucocorticoid-induced osteoporosis emphasize early fracture-risk assessment for adults receiving long-term glucocorticoid therapy. That assessment commonly considers medication exposure, fracture history, clinical risk factors, bone mineral density, and sometimes vertebral imaging. A silent vertebral compression fracture can change the clinical picture even when a person has never described a dramatic fall or a memorable injury.
Bone mineral density, usually reported as a T-score or Z-score, answers a necessary question: how much mineralized bone is present at a measured site? Lower density is associated with higher fracture risk, and density helps clinicians classify osteopenia and osteoporosis.
But steroids reveal a limitation in treating density as the whole story. Bone loss may occur rapidly, and fracture risk can rise at a given density level in people exposed to glucocorticoids. That does not make density unhelpful. It means the density number belongs inside a broader risk assessment.
The difference between a baseline and a plan to observe change
A baseline is valuable because it gives later results a reference point. Without one, it can be difficult to distinguish a longstanding low-density result from an active change during treatment.
Follow-up timing is not universal. It depends on factors such as the expected duration of steroid exposure, current bone status, fracture history, age, and whether treatment decisions are being made. The useful question is not simply, “When is my next scan?” It is, “What information would a future measurement need to clarify?”
For someone beginning an extended steroid course, the concern may be early change. For someone with known osteopenia or osteoporosis, the focus may be whether measured bone values remain stable and how fracture-risk information fits with the rest of their care. For someone with repeated short courses over years, cumulative exposure and other risks may be the issue.
Why precision matters when bone can change over months
Every measurement has some degree of variation. With bone testing, that variation matters because the change being watched may be small. If a technology has a wide precision error, a modest difference between two reports may reflect measurement noise rather than a real biological change.
This is why repeatability is more than a technical detail in steroid bone monitoring. A reliable follow-up measurement can help separate signal from noise. It also helps the clinician interpret results alongside medication exposure, symptoms, height changes, prior fractures, and other medical information.
DXA remains the established standard used widely in osteoporosis diagnosis and treatment pathways. It measures bone mineral density and has decades of clinical use behind it. Its limits are also worth understanding: a DXA result does not directly describe every feature associated with skeletal fragility, and changes in positioning, machine calibration, and other technical factors can affect serial comparisons.
What REMS adds beyond density
REMS, or Radiofrequency Echographic Multi Spectrometry, measures bone mineral density at the lumbar spine and proximal femur using radiation-free ultrasound. It then analyzes raw ultrasound signals reflected from the bone to derive an independent Fragility Score.
That distinction is meaningful. Density describes how much mineralized bone is present. The Fragility Score reflects signal patterns associated with greater skeletal fragility that density alone does not capture. REMS weighs density and Fragility Score together to estimate five-year fracture risk.
Imagine two people whose density results fall in a similar range. One may have a lower Fragility Score and a lower estimated fracture risk. The other may have a higher Fragility Score, suggesting a different fragility signal despite similar mineral density. Neither number replaces clinical judgment, but the second person has information that a density result alone could not provide.
For people using long-term glucocorticoids, that additional view can be especially relevant. Steroid exposure is one of the situations where the question is larger than “Has density crossed a diagnostic threshold?” It is also, “What does the available information suggest about fragility and fracture risk now?”
REMS is FDA-cleared and radiation-free. Its reported intra-operator precision error is below 0.5%, compared with the 0.9% to 1.9% commonly reported for DXA at the spine. That level of precision may support monitoring over shorter intervals when a clinician considers repeated assessment useful. It does not mean every small change requires action, and it does not eliminate the role of DXA, laboratory data, vertebral imaging, or a clinician’s full evaluation.
Questions that make a bone-health conversation more useful
If steroids are part of your care, it can help to bring specific questions to the conversation rather than waiting for a generic recommendation. Four questions often clarify what matters:
- How does my steroid dose, duration, and history of prior courses affect my bone-fracture risk?
- Do I have other factors that raise concern, such as menopause, prior fractures, diabetes, inflammatory disease, or cancer-treatment history?
- What does my current density result tell us, and what does it leave unanswered?
- What information would be most useful to compare over time?
These questions do not assume that a fracture is likely. They recognize that medication-related skeletal change can be silent, and that better information supports better decisions.
Mechanical loading, adequate nutrition, vitamin D status, fall risk, inflammatory disease control, and osteoporosis medications may all be part of a clinician-guided bone-health discussion. Their relevance varies by person. Monitoring does not substitute for treatment when treatment is indicated, but it gives treatment decisions and follow-up a clearer factual foundation.
Information before consequences
The purpose of monitoring is not to turn every steroid prescription into a source of alarm. Many people need glucocorticoids, benefit from them, and never experience a fragility fracture. The purpose is to avoid treating the absence of symptoms as proof that nothing is changing.
Your bones do not send a warning when remodeling shifts. A fracture is often the first event that makes an invisible process visible. Knowing your density, understanding whether there are signs of greater fragility, and placing both in a fracture-risk estimate gives you a more complete place to begin the conversation.